EMS Programme Design: Sessions, Zones and Progression
Quick Answers
- What does a EMS programme actually consist of? A planned series of sessions, each built from a defined sequence of contraction phases, with zone selection and progression review points agreed before the first appointment.
- Why does protocol design matter as much as the device? Two clinics can run the same platform and produce very different patient experiences depending on how zones are planned, how intensity progresses, and how thoroughly patients are screened.
- How is applicator placement decided? Placement follows the muscle group being targeted and the individual patient’s anatomy, and is confirmed at the consultation rather than applied from a fixed template.
- What should be reviewed between sessions? Comfort and tolerance, visible change measured against baseline photography, and whether the remaining plan still matches the patient’s stated goal.
- Can EMS be combined with fat reduction? Yes, but the two address different tissue compartments, so the sequence is a clinical decision rather than a fixed package rule.
Why Protocol Design Decides the Outcome
High-intensity focused electromagnetic technology works by inducing supramaximal muscle contractions – contractions stronger than what a patient can produce voluntarily. That is the mechanism, and it is the same mechanism in every EMS platform on the market. What differs between clinics is not the physics but the plan built on top of it: which zones are treated, in what order, at what intensity progression, with what review points, and with what the patient was told to expect.
This is why protocol design deserves as much attention as device selection. A well-chosen platform operated with an undefined protocol tends to produce inconsistent experiences, uneven records and patients who cannot tell whether the programme is working. A defined protocol turns the device into a repeatable service: the operator knows what happens in session one, session four and session eight, the patient knows what to expect, and the clinic can review outcomes against a baseline instead of memory.
For clinics building a body contouring service line, the practical question is therefore not only “which machine” but “what is our standard programme”. The sections below set out the components of that programme.
Session Structure: Three Phases
A single EMS session is not a single continuous contraction. It is structured, and the structure is what makes treatment tolerable and consistent. Most protocols can be described in three phases, whatever the specific parameters in the device’s instructions for use.
| Phase | Purpose | What the operator controls |
|---|---|---|
| Warm-up | Familiarise the patient with the sensation and prepare the muscle group before high-intensity work | Starting intensity, applicator seating, patient feedback loop |
| Supramaximal work | Deliver the contraction load the treatment is designed around | Intensity progression within the patient’s tolerance, phase duration, rest intervals |
| Recovery and close | Return the muscle group to a comfortable state and set aftercare expectations | Reduced-intensity finish, skin check, aftercare instructions, next appointment |
The warm-up phase is the one most often skipped in a busy clinic, and it is the one that most affects whether a patient returns. Supramaximal contractions are an unusual sensation; a patient who is taken to high intensity in the first minutes may complete the session but arrive at the next appointment apprehensive. Building intensity gradually costs a few minutes and protects the whole programme.
Rest intervals matter for the same reason. They allow the operator to check tolerance, reposition the applicator if it has shifted, and confirm that the patient is still comfortable. A session that runs without any check-in leaves the clinic with no record of how the patient responded, which makes the next session guesswork.
Zone Planning: Placement Follows Anatomy
EMS applicators are positioned over a muscle group, and the result depends on whether that positioning is correct for the individual patient. Anatomy varies: the same nominal zone on two patients can require different applicator orientation, different spacing and different patient positioning on the bed.
Four planning questions apply to every zone:
- Which muscle group is being targeted, and does it match the patient’s goal? A patient asking for a flatter abdomen and a patient asking for more defined abdominal musculature may need different zone emphasis, even though both point at the same area.
- Is the patient positioned so the muscle group is under load rather than relaxed? Positioning affects how the contraction is experienced and where it is felt.
- Is placement symmetrical where symmetry is the goal? For paired zones, mark and verify both sides before starting, not after.
- Does the planned zone set fit the session time the clinic has booked? Cramming three zones into a slot sized for one is a scheduling problem that becomes a clinical one.
Recording placement in the treatment note – zone, orientation, side, intensity reached – is what makes a programme reproducible. Without it, session five is designed from recollection rather than from data.
Building a Multi-Session Programme
EMS is a series-based treatment. A single session is an introduction to the sensation and a baseline; the programme is where change is pursued. Structuring that programme means deciding four things in advance.
1. A defined block. The number of sessions in a treatment block should follow the device’s instructions for use and the individual treatment plan, not a number chosen for the price list. Publish the block your clinic actually follows, and explain at consultation that response varies between patients.
2. Review points inside the block. Set at least one formal review before the block ends. This is the moment to compare against baseline photography, discuss tolerance, and decide whether the remaining sessions still serve the original goal.
3. A progression rule. Decide in advance what happens if a patient tolerates intensity well and what happens if they do not. A written rule prevents one operator pushing ahead and another holding back, which is how inconsistent results appear within a single clinic.
4. A maintenance conversation. Patients usually want to know what happens after the block ends. Maintenance intervals should be framed by response and lifestyle rather than sold as a permanent subscription, and the decision belongs at the review point, not at the first booking.
Screening Before the First Session
Screening is part of protocol, not paperwork. The authority for contraindications is the device’s instructions for use, and every clinic should work from that document rather than from a generic list copied between practices. The practical workflow is to review the IFU list with the patient, document the answers, and confirm that any implanted device, metallic implant in the treatment area, pregnancy, or condition affecting muscle contraction has been assessed before the applicator is placed.
Two habits make screening reliable. First, ask the questions in a fixed order so nothing is skipped when the clinic is busy. Second, record what the patient said rather than only that screening was completed, because a later clinical question is answered by the record, not by the checkbox.
Consent should match the programme: what the treatment does, what it does not do, that it is not a weight-loss procedure and not a substitute for exercise or diet, what sensation to expect, and what aftercare applies. A consent form that overstates the outcome creates the dissatisfied patient that no protocol can rescue.
Tracking Outcomes Without Overpromising
Body contouring outcomes are difficult to judge by eye, which is why measurement has to be planned rather than improvised. Three practical instruments cover most of what a clinic needs.
- Standardised photography – same position, same distance, same lighting, same time of day where possible, taken at baseline and at each review.
- Consistent measurement – the same tape points, recorded by the same method, with the limitation of tape measurement acknowledged rather than hidden.
- Patient-reported change – recorded in the patient’s own words at each review, because function and confidence often move before a tape measure does.
The discipline here is presentational as much as clinical. Comparing a relaxed baseline photograph with a tensed review photograph flatters the treatment and destroys trust when the patient notices. Consistency protects the clinic as much as it protects the patient.
Equally, the language used at review matters. EMS builds and tones muscle; it does not remove fat, and it does not replace exercise or diet. A clinic that says so plainly at consultation finds that reviews are straightforward, because the patient was never promised something the mechanism cannot deliver.
Sequencing With Fat Reduction
Body contouring consultations frequently end with a plan that includes more than one technology. The clinical logic is simple once the tissue compartment is named: EMS addresses muscle, while cryolipolysis, laser lipolysis and microwave devices address fat or skin. They are complements, and pairing them is a legitimate reason a clinic can offer a broader programme than a single-modality competitor.
The sequencing decision should follow the patient’s priority rather than the clinic’s package structure. If the primary concern is muscle definition under a layer of fat, reducing the fat layer first may make the muscle work more visible. If the primary concern is tone and support, starting with muscle may be the better first block. Either way, document the rationale, leave a defined interval between modalities, and confirm that the combination is appropriate under both devices’ instructions for use.
What to avoid is the package sold as a single indivisible unit with no clinical explanation. Patients increasingly ask why a sequence is ordered the way it is, and a clinic that can answer in tissue terms wins the consultation.
Staff Competency and Training
Protocol only works if the people delivering it are trained to the same standard. That means more than knowing how to switch on the device. An operator should be able to explain the mechanism in plain language, screen against the contraindication list, position a patient for a specific zone, judge intensity progression from patient feedback, recognise when to stop, and record a session in a way another operator could reproduce.
Training format varies by supplier and region, so confirm who delivers it, whether it covers protocol building as well as device operation, and whether refresher training is available. A useful internal rule is to have a new operator observe a full programme block before treating independently, and to review their first cases against the clinic’s standard protocol.
FABE: Protocol-Relevant Features
| Feature | Advantage | Benefit |
|---|---|---|
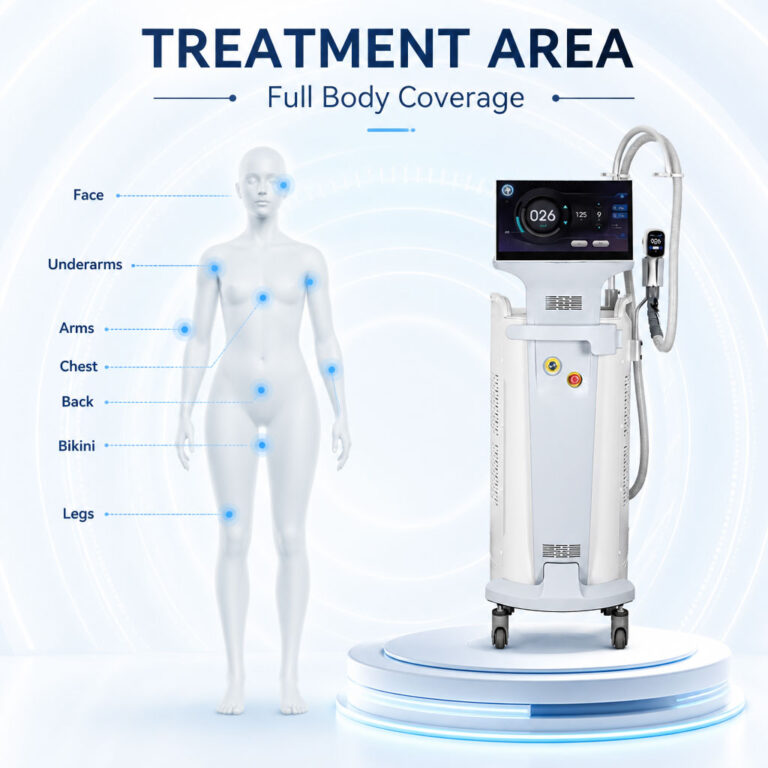
| Applicator set covering multiple muscle groups | Zone planning can follow the patient’s goal rather than the device’s single fixed area | Clinic can build several programme types; patient can address more than one concern |
| Adjustable contraction intensity | Operator can progress within tolerance and hold a level that the patient can complete | Better session tolerance and more consistent attendance across the block |
| Defined contraction phases | Session structure is repeatable between operators | Consistent patient experience regardless of who is on shift |
| Non-invasive, no downtime | Patient returns to normal activity immediately | Sessions fit around work; clinic can schedule without recovery-room capacity |
| Complements fat-reduction devices | Muscle and fat can be addressed in one programme | Higher-value body transformation packages with a clinical rationale |
| Manufacturer training and protocol support | Clinic can standardise before scaling to multiple operators | Faster ramp-up for new staff and fewer protocol deviations |
Manufacturing and Training Support Behind the Protocol
The Emslim-type EMS body contouring machine is manufactured by Beijing JONTELASER Technology Co., Ltd. and marketed under the JT MED brand. The company was founded in 2004 and exports to more than 50 countries. Its quality system is ISO 13485 certified with MDSAP participation, and device compliance is aligned wit FDA Support for clinic buyers includes operator training, OEM/ODM options, marketing materials and after-sales service.
For a clinic standardising a protocol, the manufacturer relationship matters at three points: whether training covers protocol building rather than operation alone, whether applicators and consumables are available for the zones in the programme, and how service requests are routed in the clinic’s country. Ask those three questions before comparing price lists.
Frequently Asked Questions
Who should design the protocol – the supplier or the clinic? The supplier provides device capability and training; the clinic owns the protocol, because it has to reflect the patient population, the operators and the schedule the clinic actually runs.
How long does a single session take? Session length depends on the number of zones treated and the phases set in the device’s instructions for use. Book the slot from your own protocol rather than from a supplier’s headline figure.
Should a patient book the whole block upfront? Booking a block is common, but the review point inside the block should be genuine – the patient should understand they can stop or adjust the plan at that review.
Can two zones be treated in one session? Yes where the protocol and the device’s instructions for use allow it, but session time and patient tolerance set the practical limit.
What patient positioning is required? Positioning should place the target muscle group under load and keep the applicator stable. It is confirmed per zone at the consultation, not assumed from the treatment name.
How do you judge whether contraction intensity is appropriate? From the patient’s reported sensation and ability to complete the phase, within the intensity range the device’s instructions for use permit.
What belongs in the treatment note? Zone, side, applicator orientation, intensity reached, phase durations, patient feedback and any deviation from protocol – enough for another operator to reproduce the session.
What if a patient feels very little? Recheck applicator placement and positioning first, then review intensity within the permitted range. If the sensation remains unusual, document it and reassess at the next session rather than escalating intensity to force a response.
Is there downtime between sessions? No incisions are involved, so patients normally return to ordinary activity immediately; transient muscle soreness can occur.
How should maintenance be scheduled? By assessed response at the review point and by the patient’s own goals, not by an automatic recurring charge.
What should a new operator complete before treating independently? Device training, a full observed programme block, and a review of their first cases against the clinic’s written protocol.
What should a clinic request when standardising protocol? The instructions for use, the applicator and consumable list by zone, training scope and format, service routing for your country, and written confirmation of the certification relevant to your market.
Next Step
Contact the JT MED export team for the Emslim-type EMS specification sheet, the applicator list by treatment zone, and details of the operator training programme, so your clinic can build a written protocol before the first patient is booked.